
INTRODUCTION
Defining adverse food reactions:
An adverse reaction to food is any undesirable response that happens after eating or being exposed to food. There are two main categories:
Food Allergy: The immune system is involved
Food Intolerance: The immune system is not involved
Examples of food intolerance:
Metabolic: lactose intolerance. Too little lactase means lactose isn’t broken down, causing bloating, gas and diarrhoea after dairy.
Pharmacologic - bioactive compounds in food affect sensitive individuals.
Histamine Intolerance: reduced diamine oxidase (DAO) activity leaves histamine intake outstripping breakdown. Causes headache, flushing, hives and GI upset.
Tyramine Sensitivity: Tyramine, found in aged cheeses and cured meats, can trigger migraines in susceptible individuals.
Toxic-
Food posioning - live bacteria, viruses, or parasites (eg salmonella, campylobacter, norovirus) cause the illness.
Preformed toxins - eg. Clostridium botulinum, which can cause severe illness.
Scromboid poisoning - bacteria in spoiled tuna, mackerel, sardines or anchovies convert histidine to histamine. Cooking kills the bacteria but doesn’t destroy the histamine. Symptoms mimic allergy (flushing, headache, bronchospasm, GI upset), start within 90 minutes and settle within 3–36 hours. Because the histamine is already in the fish, everyone who eats the same dish can become unwell at around the same time, which can look like a ‘food allergy’ outbreak.
FOOD ALLERGY INTRODUCTION
Food allergies themselves can be classified based on the immune mechanism involved:
IgE-mediated: These involve IgE antibodies (Type I hypersensitivity reactions)
Non-IgE mediated: These involve other cells of the immune system, such as T cells
Mixed IgE and non-IgE mediated: These involve both IgE and cellular mechanisms
Understanding whether a food reaction is IgE-mediated or non-IgE-mediated is important for proper diagnosis and management
TYPE 1 HYPERSENSITIVITY REACTION (IgE MEDIATED)
Mechanism:
This is the classic type of food allergy many people are familiar with.
It occurs when the body's immune system produces IgE antibodies specific to certain food proteins.
Upon subsequent exposure to the food, these IgE antibodies bind to mast cells and basophils, triggering the rapid release of mediators like histamine, which cause immediate symptoms.
Presentation:
This is the commonest type of food allergy (affects about 5% of young Irish children and about 2% of older children and adults). Patients may experience a spectrum of severity, from mild skin symptoms or mouth itching to anaphylaxis, which is a severe, potentially life-threatening systemic reaction.
Timing of Onset:
Symptoms develop very quickly after exposure, typically within minutes, and generally within 2 hours of ingesting the food.
Even very small amounts of the food can elicit a significant reaction
In severe cases a reaction can occur due to airborne exposure
Symptoms:
These reactions can affect one or multiple organ systems
Skin:
Acute urticaria and angioedema are common
Gastro-intestinal:
Oral/pharyngeal itching or swelling, immediate vomiting, nausea, abdominal cramps, or diarrhoea
Respiratory:
Rhinitis, hoarseness, stridor/laryngeal oedema, cough, dyspnoea, chest tightness, wheezing
Cardiovascular:
Pallor, cold sweats, heart palpitations, pre-syncope/syncope, tachycardia, hypotension, or shock
Neurological:
Anxiety, a "feeling of impending doom," change in behaviour, irritability, apathy, lethargy, seizures, syncope/loss of consciousness
On their own urticaria and angioedema are ‘minor’ symptoms
Cough/hoarseness (indicating upper airway obstruction) or feeling faint (cardiovascular collapse) should be treated as potentially severe symptoms
Type 1 hypersensitivity reactions can occur in different ways which will be discussed later:
In the image below you can see the 8 common foods implicated in Type I food allergy
Nut allergy persists for life in approximately 80% of cases
Milk and egg allergy persists in just 10-20% of cases
NON-IgE MEDIATED FOOD ALLERGY
These are delayed in onset (usually type IV hypersensitivity)
Mechanism: These reactions do not involve IgE antibodies. Instead, they are mediated by other parts of the immune system, often T cells.
Timing of Onset: Symptoms are delayed, typically occurring hours to days after ingesting the food. This delayed onset can make it more difficult to elicit from the history compared to IgE reactions
Presentation:
A small dose may be tolerated but incremental doses are not tolerated. Symptoms are more diffuse and include GI symptoms and worsening eczema
Non-IgE mediated food allergies lack reliable laboratory tests for diagnosis.
Standard allergy assessments, such as skin prick testing and specific IgE measurements, are not useful.
In cases where there is clinical suspicion exclusion of the food for 2-4 weeks with reintroduction is the only supportable diagnostic and possibly therapeutic intervention
If symptoms get better when the food is removed and then return again when the food is reduced then that is diagnostic for food allergy
Ideally this would be supervised by a dietitian.
Symptoms:
Non-IgE-mediated food allergies predominantly present with gastrointestinal symptoms, particularly in infants. These can include bloating, reflux, colic, persistent crying, diarrhoea (sometimes with blood or mucus), abdominal pain, loose stools, food aversion, failure to thrive.
Eczema exacerbations may occur, although isolated delayed eczema flares caused by food appear uncommon.
There are other GI syndromes that can occur due to delayed type food allergy which I briefly mention later:
Food protein-induced enteroloitis syndrome (FPIES)
Food protein-induced allergic proctocoolitis (FPIAP)
Food protein-induced enteropahty
Eosinophilic Oesophagitis (mixed IgE and non-IgE mediated allergy)
MIXED IGE AND NON-IGE MEDIATED FOOD ALLERGY
To further complicate things, some patients with food allergies can have both IgE-mediated and non-IgE-mediated allergies at the same time.
Patients with this may present with immediate reactions like urticaria alongside delayed features such as eczema flares.
A structured clinical approach including a careful history, targeted allergy testing, and appropriate use of elimination trials is therefore key to tease out these difficult cases.
FOOD ALLERGIES AND ECZEMA
There is a temporal association between food allergy and atopic eczema
Food allergy is more likely in infants with early-onset eczema (before 6 months) and in those with more severe disease.
Atopic march:
The atopic march describes the typical sequence of atopic conditions through childhood, although not every child follows it.
Eczema and IgE-mediated food allergy usually appear first, in infancy.
Many children outgrow eczema and food allergies such as egg and milk, but peanut and tree nut allergy often persist.
Asthma and allergic rhinitis often follow in later childhood, and early, severe eczema increases the risk. Allergic rhinitis is the commonest atopic condition in adults.

Dual allergen exposure hypothesis:
The dual allergen exposure hypothesis proposes that the risk of food allergy depends on the balance between skin exposure and oral exposure to the allergen.
Skin exposure, especially through inflamed skin in eczema, tends to promote sensitisation. This is more likely with low-dose exposure from the environment. Skin inflammation and the altered immune environment in eczema favour an IgE-mediated response.
Oral exposure through the gut tends to promote tolerance, particularly at higher doses and before sensitisation through the skin.
Once sensitisation has occurred, the risk of a clinical allergic reaction rises. Early oral exposure builds tolerance, whereas repeated exposure through inflamed skin makes an abnormal immune response more likely.

LEAP STUDY
The LEAP study (NEJM, 2015) tested whether early peanut introduction prevents peanut allergy.
It enrolled 640 high-risk infants, with severe eczema and/or egg allergy.
At 4 to 11 months they were randomised to eat peanut regularly or avoid it until age five.
At age five, peanut allergy was 81% less common in the peanut-eating group than in the avoidance group (relative reduction).
The benefit lasted after a year of peanut avoidance.
Current advice is to introduce peanut from around four to six months in high-risk infants, alongside other solid foods.
If the eczema is not severe, around six months is appropriate.
Whether to test first varies between guidelines. US guidance suggests considering it in severe eczema or egg allergy, whereas UK guidance does not require it.
CLINICAL WORKUP
The first and most important step when assessing a child with suspected food allergy is a detailed allergy-focused clinical history.
This helps establish the likelihood of a genuine food allergy (the pre-test probability), guides the decision to undertake further investigations, and provides the context needed to interpret any subsequent test results.
Why is Food Allergy Difficult to Diagnose in Children with Eczema?
Establishing whether food allergy contributes to a child's eczema can be particularly challenging, especially when delayed eczematous reactions are suspected.
There are several reasons for this:
Eczema naturally fluctuates: Atopic eczema follows a relapsing and remitting course. Delayed eczema exacerbations occurring hours or days after food ingestion can therefore be difficult to distinguish from the natural fluctuations of the disease.
Eczema may be inadequately treated: Suboptimal treatment or poor adherence can contribute to persistent inflammation, which may be incorrectly attributed to food allergy.
Food sensitisation is common: Children with eczema, particularly those with more severe disease, frequently have elevated total IgE and positive food-specific IgE tests without clinically relevant food allergy.
For these reasons, a careful clinical history, assessment of eczema control and appropriate interpretation of allergy investigations are essential.
Taking a Food Allergy History
Four key areas to explore in a child with suspected food allergy
1. Reaction and Exposure Details
- Which food was suspected?
- How soon after ingestion did symptoms develop?
- What symptoms occurred?
- How severe was the reaction? Was treatment required?
- How much of the food was eaten?
- Was the food raw, cooked or baked?
- Has the reaction been reproducible?
- Were there any cofactors, such as exercise, illness or NSAIDs?
2. Atopic Eczema History
- At what age did eczema begin?
- How severe is the eczema?
- What treatments are being used, and how consistently?
- Is eczema adequately controlled?
- Is there a reproducible relationship between food ingestion and eczema worsening?
3. Gastrointestinal Symptoms and Nutrition
- Are there gastrointestinal symptoms associated with ingestion?
- Are there feeding difficulties or food aversion?
- Are there concerns regarding weight gain or growth?
- Are any foods currently being avoided, and why?
4. Personal and Family History
- Does the child have asthma, allergic rhinitis or other allergies?
- Are there other relevant medical conditions?
- Is there a family history of food allergy or atopic disease?
Optimise eczema treatment first
Ensure that eczema is adequately treated before attributing persistent or fluctuating disease to food allergy. Poorly controlled eczema can be mistaken for food-triggered flares.
Reproducibility is particularly important
A consistent reaction following ingestion supports food allergy. If a child regularly tolerates an age-appropriate portion of a suspected food, allergy to that food in that form is unlikely. However, occasional reactions can occur with cofactor-dependent allergies.
Food preparation matters
Heating, particularly extensive baking, can reduce the allergenicity of some proteins, notably in milk and egg. Ask whether the child tolerates baked forms despite reacting to less-heated forms.
Consider cofactors
Exercise, intercurrent illness, NSAIDs and other cofactors may lower the threshold for allergic reactions. These are especially useful to consider when reactions are inconsistent.
Following a detailed clinical history, consider whether the suspected food-related reaction fits one of three patterns: immediate, combined immediate and delayed, or isolated delayed.
As this will help guide further investigation and management
Immediate
IgE-mediated symptoms such as urticaria, angioedema, vomiting or respiratory symptoms.
Combined
An immediate allergic reaction followed by an eczema exacerbation hours later.
Delayed
An isolated eczema exacerbation without preceding immediate allergic symptoms.
DIAGNOSIS OF IgE MEDIATED FOOD ALLERGY
If the clinical history suggests an IgE-mediated food allergy, skin prick testing or specific IgE blood testing can help support the diagnosis.
Sensitisation ≠ Allergy
Sensitisation means that a person has detectable food-specific IgE antibodies, whereas food allergy means that exposure to the food causes a clinical allergic reaction.
A positive skin prick test or specific IgE blood test does not necessarily indicate a clinical food allergy.
SKIN PRICK TESTING
Skin prick testing is a quick method of detecting IgE sensitisation to a suspected food allergen.
How it works: A drop of allergen extract (or sometimes fresh food) is placed on the skin and gently pricked. After approximately 15 minutes, any resulting wheal is measured. Antihistamines should generally be withheld for 5–7 days before skin prick testing, although shorter intervals may be sufficient for some medications. Follow local allergy testing protocols.
Interpretation: A wheal ≥3 mm larger than the negative control is generally considered positive. Larger wheals increase the likelihood of clinical allergy, and food-specific cut-offs can help estimate this probability.
Limitations: A positive test indicates sensitisation, not necessarily clinical allergy. Children with eczema frequently have positive tests to foods they can tolerate.
Testing should therefore be guided by the clinical history, rather than ordering broad food allergy panels, which can lead to false-positive interpretations and unnecessary dietary restrictions.
SPECIFIC IgE TESTING
Specific IgE testing is a blood test that measures IgE antibodies directed against particular food allergens. It was previously referred to as RAST testing.
How it works: A blood sample is analysed to measure food-specific IgE concentrations, reported in kU/L.
Interpretation: Higher specific IgE levels generally indicate a greater likelihood of clinical allergy. Food-specific thresholds associated with a high positive predictive value (e.g. 95%) have been established for certain allergens, although these vary with age and the population studied.
Limitations: Like skin prick testing, a positive result indicates sensitisation rather than necessarily confirming clinical allergy. Testing should therefore be guided by the clinical history, avoiding broad allergy panels that may lead to unnecessary dietary restrictions.
Specific IgE testing is particularly useful when skin prick testing is impractical, such as in children with extensive eczema or those unable to stop antihistamines.
Total IgE is not routinely useful in diagnosing food allergy.
In general testing for total IgE is not helpful in the diagnosis of food allergy especially in atopic eczema patients
COMPONENT-RESOLVED DIAGNOSTICS
Traditional allergy tests (skin prick testing and specific IgE blood tests) use extracts containing a mixture of proteins from a food or pollen.
However, different proteins have different clinical implications:
Species-specific allergens: Proteins associated with a particular food (e.g. Ara h 2 in peanut). These are often stable and more strongly associated with primary food allergy.
Cross-reactive allergens: Proteins found across different foods and pollens (e.g. PR-10 proteins and profilins). Sensitisation may arise from pollen exposure and can cause positive food allergy tests without clinically significant food allergy.
CRD measures IgE against individual proteins, helping distinguish primary food allergy from pollen-related cross-reactivity.
For example, in peanut testing:
Ara h 2: Strongly associated with primary peanut allergy.
Ara h 8: Cross-reacts with birch pollen and is more commonly associated with mild oral symptoms (pollen-food syndrome) or no symptoms.
Plant food allergens - strong, stable allergens. Positive IgE to these often means a true food allergy
Cross-reactive allergens - Proteins shared between pollens and foods. Positive IgE often does not mean a real food allergy and patients may tolerate the food
EAACI guidelines (2023) recommend considering the following components alongside standard testing in suspected food allergy
BASOPHIL ACTIVATION TEST (BAT)
The basophil activation test (BAT) is a more specialised blood test that measures how a patient’s basophils react when exposed to a suspected allergen
How it works: A blood sample is exposed to the suspected allergen in the laboratory. The percentage of basophils that become activated is then measured using flow cytometry.
Unlike skin prick testing or specific IgE testing, which identify sensitisation, BAT measures an actual cellular response to the allergen.
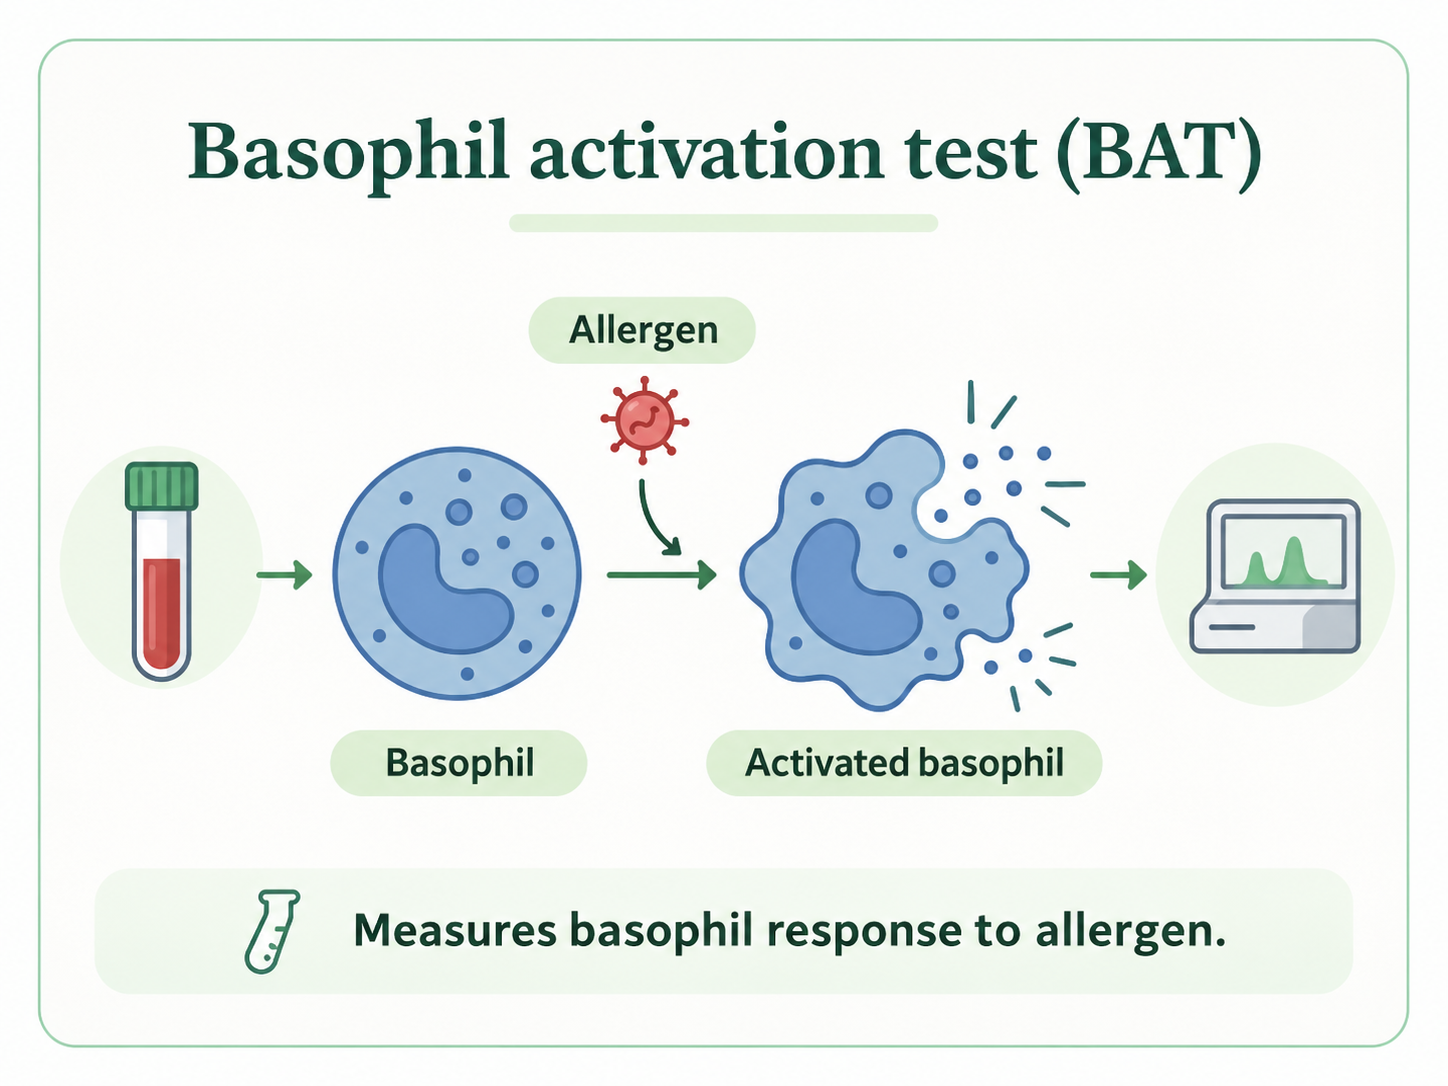
Clinical use: BAT can help distinguish genuine food allergy from sensitisation, particularly when the clinical history and initial allergy tests are inconclusive.
The EAACI guidelines (2023) conditionally recommend BAT for suspected peanut and sesame allergy when standard testing has not provided a clear diagnosis.
Limitations: Although BAT has shown good diagnostic performance, it is more expensive and not widely available outside specialist centres. An oral food challenge may still be required when results remain inconclusive.
Putting it together
The diagnosis of IgE-mediated food allergy begins with a careful clinical history.
The aim is to decide whether the reaction sounds consistent with an immediate-type allergy, identify the most likely culprit food, and then use targeted testing to support or refute that suspicion.
In practice, the process is usually as follows:
Start with a detailed allergy-focused history
Decide whether an IgE-mediated reaction is suspected
Formulate a hypothesis about the most likely trigger food(s)
Perform targeted testing only (skin prick testing and/or specific IgE) - component testing can be added to refine the diagnosis if available (particularly for peanut, cashew, hazelnut)
Interpret the results in the context of the history
If the history is convincing and testing supports sensitisation to the suspected food, the diagnosis may be confirmed.
If there is no convincing history and no evidence of sensitisation, IgE-mediated food allergy is unlikely.
If the history and test results are inconclusive or conflicting, the next step may be an oral food challenge.
Oral Food Challenge
An oral food challenge (OFC) is the gold standard for diagnosing or excluding food allergy, particularly when the clinical history and allergy test results are inconclusive.
How it works: The patient eats gradually increasing amounts of the suspected food under close medical supervision, usually at intervals of 20–30 minutes.
The patient is monitored throughout for signs of an allergic reaction, with emergency treatment available if required.
Interpretation:
Positive challenge: An allergic reaction occurs, confirming food allergy when the symptoms meet the diagnostic criteria.
Negative challenge: The patient tolerates the full challenge dose without an allergic reaction, making allergy to that food unlikely.
Clinical use: Oral food challenges are particularly useful when allergy tests are positive but the clinical history is unclear, or when assessing whether a child has outgrown a previously diagnosed food allergy.
Limitations: As allergic reactions, including anaphylaxis, can occur, challenges must be performed in an appropriately equipped clinical setting under trained medical supervision.
MILK ALLERGY
Cow's milk allergy is a very common presentation of food allergy in early childhood, with almost all cases presenting within the first year of life
Prevalence estimates can vary due to potential overestimation due to misinterpretation of symptoms, particularly in non-IgE mediated (delayed) allergy, where common infant issues like eczema, reflux, or abnormal stools might be mistaken for food allergy
The prevalence of CMA in children living in the developed world is approximately 2% to 3%, making it the most common cause of food allergy in the paediatric population
Among breastfed infants the prevalence is lower (0.5 %)
The EuroPrevail study was a big prospective birth cohort study with about 12,000 children across Europe and this reported that milk allergy affects aobut 1% of children in Europe up to the age of 2 years, with the highest prevelence of non-IgE mediated allergy being seen in the UK
The majority of children will outgrow their milk allergy
Non-IgE mediated allergy generally resolves faster than immediate (IgE-mediated) allergy
The EuroPrevail data showed about 70% of IgE mediated allergy was resolved within one year of diagnosis and almost 100% of non-IgE mediated allergy
It was initially felt that milk allergy only persists to preshcool age but it can persist longer into adolescence
It's important to note that milk is now the biggest single food cause of fatal food anaphylaxis
Distinguishing Immediate (IgE-mediated) and Delayed (Non-IgE mediated) Reactions
Diagnosing immediate (IgE-mediated) milk allergy is generally much easier. Reactions occur very quickly after consumption of milk, typically within minutes up to a couple of hour, and can often be confirmed with allergy testing
In contrast, delayed (non-IgE mediated) milk allergy is much trickier to confirm. Symptoms are delayed, and can occur days after exposure
Also the symptoms can be non-specific and include flares of eczema or GI symptoms which can occur in infants without food allergy and can include more vague issues like eczema or non-specific GI symptoms
Diagnosis relies heavily on a clinical history and is primarily confirmed through a strict elimination diet followed by reintroduction
Management of milk allergy:
Management differs significantly based on whether the allergy is IgE-mediated or non-IgE mediated
The mainstay of treatment is to remove cow's milk protein from the diet while ensuring the nutritional adequacy of alternatives
Education is key for managing milk allergy and knowing how to respond to an allergic reaction
If immediate allergy is suspected, referral to an allergy service is recommended
Immediate (IgE-mediated) Allergy:
Managed with milk avoidance
Ensuring the individual has emergency medication is crucial, including antihistamine. Some infants may need adrenaline pens, particularly if they have multiple food allergies or a history of a severe reaction to milk.
A written emergency management plan (e.g., BSACI allergy action plan) should be provided to families and schools
Human breast milk is best for the baby
Majority of infant formulae made using modified cow’s milk and contain cow’s milk protin
Cow’s milk protein allergy varies from 2-7.5%.
Resolution excpected in between 75 and 90% of cases before 5-6 years of age
Rates may be lower in severe cases
The diagnosis of IgE mediated milk allergy is usually quite straightforward
Can be IgE mediated or non IgE mediated:
IgE mediated- rapid onset urticarial, swerlling, airway symptoms
Non IgE mediated- delayed gastrointestinal and skin symptoms
Most children present before 6-7 months of age (during this time milk is major fodd so other food allergies usually don’t need to be considered)
Exclusively breast fed infants with cow’s milk allergy may respond to time defined complete maternal exclusion of cow’s milk (should be supervised by dietician)
Infant formula:
Usually contains cow’s milk protein
Some contain extensively hydrolysed protein- more hypoallergenic
Amino acid based formulas- even more hypoallergenic
So amino acid formulas may be indicated in those presenting younger with severe and persistent allergy
No place for lactose free formula
Other mammalian milk (goat, sheep, camel, donkey, horse etc) and/or plant based milk (soy, rice, oat, almond, coconut) not indicated
-some are not nutritionally complete
-some cross react with cow’s milk and cause reactions
ORAL ALLERGY SYNDROME (POLLEN FOOD SYNDROME)
Oral allergy syndrome (OAS) is an IgE-mediated food allergy
Typically affects individuals who have allergic rhinitis to pollen (eg birch, grass, ragweed)
Symptoms typically occur within minutes with itching, tingling or mild swelling in the lips, mouth and throat
The condition is usually mild and self-limited, but rarely, more serious reactions (eg anaphylaxis) can occur
OAS is a type of cross-reactivity where the immune system mistakes proteins in the fruit/vegetable for similar proteins in pollen
Common triggers include:
Birch pollen allergy → apple, pear, carrot, celery, hazelnut.
Grass pollen allergy → melon, tomato, orange.
Ragweed pollen allergy → banana, cucumber, melon.
Cooking the food often prevents the reaction, as the proteins causing the problem are broken down by heat
Peeling the fruit can help as in fruits like apples, peaches and pears where the proteins that cross-react with pollen allergens are often most abundant in the peel and outer layers
In some foods (like celery or nuts) the allergenic proteins can be more stable and present throughout the food so peeling or cooking may not always prevent reactions
Diangosis is usually based on history but can be supported by skin prick testing or specific IgE testing
Management includes avoiding the raw triggering foods, eating them cooked if possible, and having antihistamines available if needed.

CONTACT URTICARIA
Contact urticaria is the rapid development of wheals (hives), redness, and sometimes swelling at the site where the skin touches a triggering substance.
It is classified into two types:
Immunological contact urticaria: IgE-mediated hypersensitivity (true allergy, e.g., latex, raw foods).
Non-immunological contact urticaria: Direct histamine release without immune sensitization (e.g., from chemicals like benzoic acid, nettle stings).
Symptoms typically appear within minutes (often within 30 minutes) of exposure
It usually presents as well-demarcated wheals or erythema, sometimes with burning, stinging, or itching.
In severe cases (especially in immunological contact urticaria), systemic symptoms can occur: generalized urticaria, angioedema, bronchospasm, hypotension (risk of anaphylaxis).
Common triggers include:
Proteins: latex, raw meats, fish, fruits, vegetables.
Chemicals: preservatives, fragrances, disinfectants.
Plants: nettles, certain occupational exposures.
Diagnosis relies mainly on clinical history and exam, open application tests and prick tests. Specific IgE testing can be supportive
Management involves avoiding the trigger, anti-histamines for symptomatic control and epinephrine should be available if there’s a risk of anaphylaxis
Occupational contact urticaria to food proteins is important to be aware of in food handlers
FOOD-DEPENDENT EXERCISE-INDUCED ANAPHYLAXIS (FDEIA)
FDEIA is a distinct IgE-mediated allergy where both food ingestion and exercise are needed to trigger a reaction.
Eating the food alone or exercising on an empty stomach does not cause symptoms; the combination is necessary.
Symptoms typically develop during exercise, within 2–4 hours after eating the trigger food.
Clinical signs include flushing, urticaria, angioedema, and potentially full anaphylaxis (hypotension, bronchospasm).
The most common trigger is wheat, specifically the omega-5 gliadin protein (detectable via component-resolved IgE testing).
Other reported triggers include shellfish, celery, soy, and other foods.
Cofactors like NSAIDs and alcohol can lower the threshold, making reactions more likely.
Management involves avoiding exercise after eating trigger foods and avoiding cofactors like NSAIDs/alcohol around meals containing these foods.
Patients should be prescribed an epinephrine auto-injector and educated on anaphylaxis management.
Exercise challenge tests can confirm the diagnosis but are high-risk and should only be done in specialist centers.
FOOD PROTEIN INDUCED ENTEROCOLITIS SYNDROME
Considered a prototypical non-IgE mediated food allergy
Typically affects infants
Presents with characteristic delayed, repetitive, profuse vomiting occuring about 1-4 hours after ingesting the trigger food, this is quicker then the other delayed allergies
Can lead to lethargy, pallor and sometimes dehydration and even shock in severe cases
Diarrhoea can follow hours later
Does not cause hives or anaphylaxis
Common triggers- cow’s milk, soy, rice, oat
Diagnosis relies on history and an oral food challenge is the definitive test if history is unclear
FPIES usually outgrown by 3-5 years of age
FOOD PROTEIN-INDUCED ALLERGIC PROCTOCOLITIS
Benign, non-IgE allergy seen commonly in young infants (often breastfed), causing blood-streaked mucus in the stools due to inflammation in the colon. The main trigger is usually cow's milk protein
Infants are usually otherwise well.
It often resolves by 1 year of age
FOOD PROTEIN-INDUCED ENTEROPATHY
Rarer
Chronic ingestion of a food protein leads to malabsorption, chronic diarrhoea, vomiting and failure to thrive
It improves upon elimination of the offending protein
EOSINOPHILLIC OESOPHAGITIS
Chronic, immune mediated disease of the oesophagus
Often considered a mixed IgE and non-IgE mediated condition
Triggered by food allergens cuasing eosinophil-rich inflammation in the oesophageal lining
Symptoms depend on age but commonly include difficulty swallowing (dysphagia) and food impactions (food getting stuck) in older patients while younger children may have difficulty feeding or poor growth
Patients with EoE often have other atopic conditions like eczema or asthma
Common food triggers include milk, egg, wheat, soy, nuts, seafood
Diagnosis requires endoscopy with biopsies showing eosinophil coutns
EoE is a chronic conditions and typically not outgrown

Possible things for me to add or work on:
SPT to peanut:
5mm - sensitivity 92.9%, Specificity 94%
8mm - sensitivity 25.4%, specifficity 98.5%
Low level positive tests have a relatively low positive predictive value (50%) for food allergy. As a result ordering such tests should be done with caution and should only be tested for 2 or 3 suspected foods